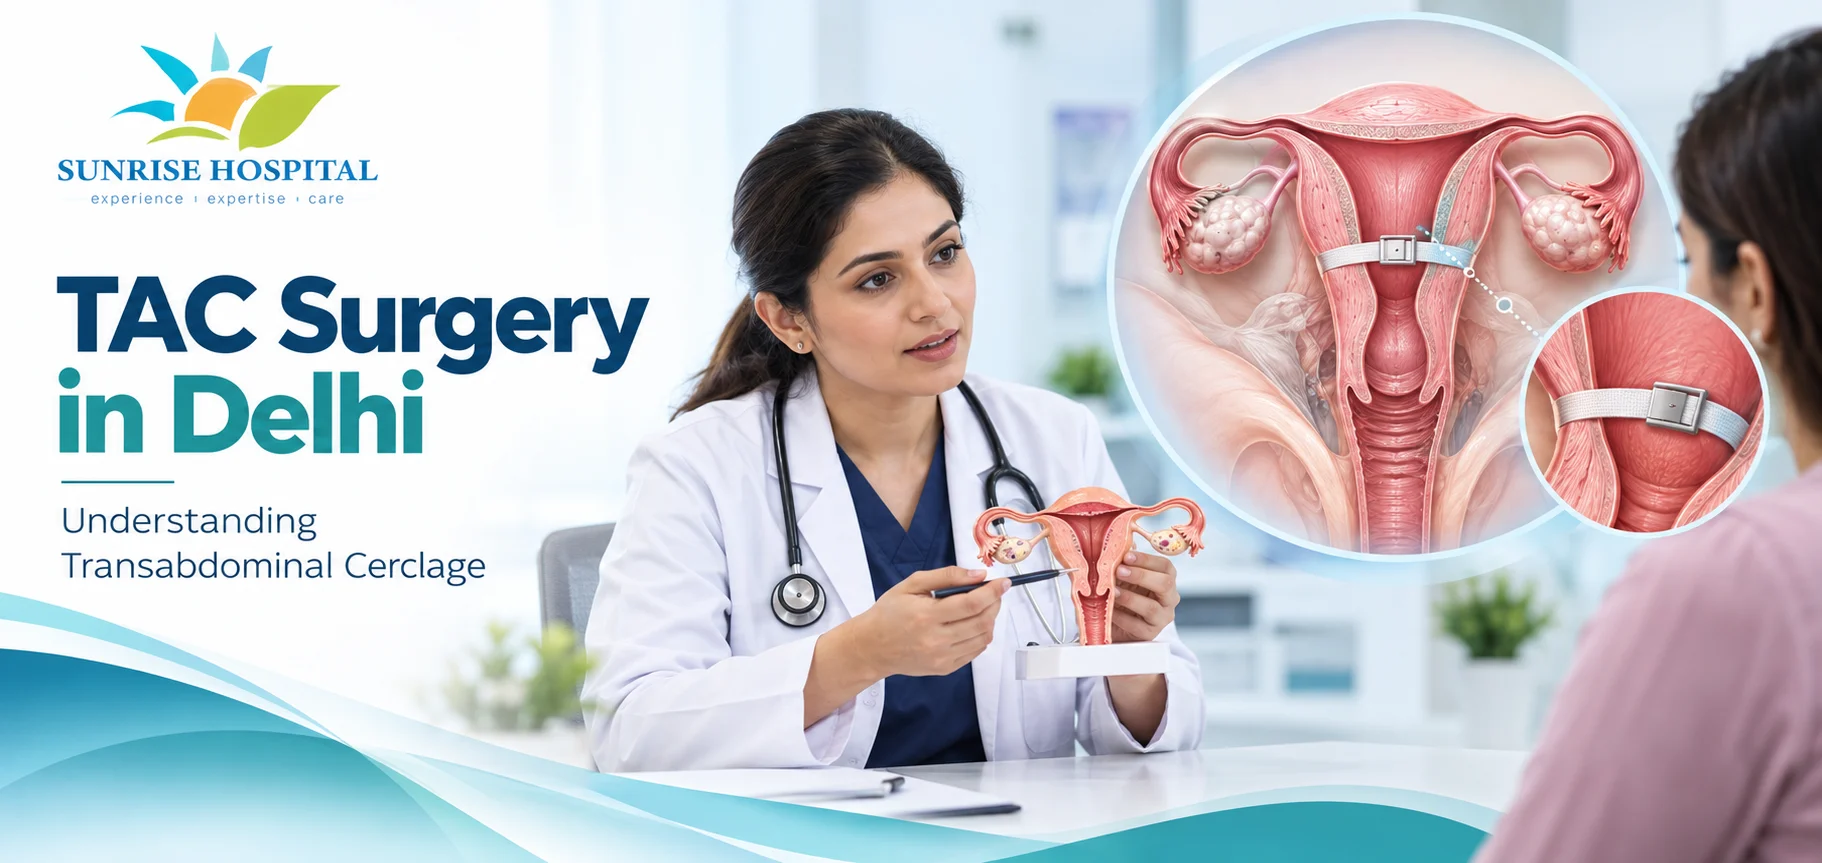
TAC Surgery in Delhi: Who May Need Transabdominal Cerclage?
TAC surgery in Delhi may be considered for selected women with cervical insufficiency who have experienced a pregnancy complication despite a previous vaginal cervical cerclage, or whose cervical anatomy makes a vaginal stitch unsuitable. Transabdominal cerclage (TAC) is a surgical procedure in which a strong stitch is placed around the cervix through an abdominal approach to help support the cervix during pregnancy.
However, TAC is not necessary for every woman with a short cervix, a previous miscarriage or a high-risk pregnancy. The decision depends on the patient's obstetric history, previous cerclage outcomes, cervical anatomy, pregnancy status and specialist assessment.
Women researching transabdominal cerclage in Delhi should understand when the procedure may be appropriate, how it differs from vaginal cerclage, what risks it involves, and how it can affect future pregnancy and delivery planning.
At Sunrise Hospital, Kalindi Colony, New Delhi, patients can contact the hospital to enquire about consultation availability and the appropriate specialist pathway for cervical insufficiency and cerclage-related concerns.
What Is Transabdominal Cerclage (TAC)?
Transabdominal cerclage, commonly known as TAC or abdominal cerclage, is a surgical procedure used in selected patients with cervical insufficiency. During the procedure, a stitch is placed around the cervix through an abdominal surgical approach rather than through the vagina.
The cervix is the lower part of the uterus that opens into the vagina. During a typical pregnancy, it remains closed until labour approaches. In cervical insufficiency, the cervix may shorten or open prematurely, sometimes without noticeable contractions. This can increase the risk of second-trimester pregnancy loss or spontaneous preterm birth.
A cervical cerclage aims to provide mechanical support to the cervix. The two main approaches are:
- Vaginal cerclage: A stitch is placed around the cervix through the vagina. It is the more common approach for appropriately selected patients.
- Transabdominal cerclage (TAC): A stitch is placed higher around the cervix through abdominal surgery. It may be considered when a vaginal cerclage has failed or is technically unsuitable.
TAC is a specialised surgical option that requires individual assessment. It carries surgical risks and usually means that delivery must take place by caesarean section. The expected benefits and limitations should be discussed with the treating specialist before proceeding.
Who May Need TAC Surgery?
The need for transabdominal cerclage depends on a woman's pregnancy history, cervical anatomy, and previous treatment outcomes. A specialist may discuss TAC in the following situations.
1. Women with a previous failed vaginal cerclage
One important reason to consider TAC is a previous pregnancy in which a vaginal cerclage was placed, but the patient subsequently experienced a spontaneous singleton delivery before 28 weeks of gestation.
The Society for Maternal-Fetal Medicine (SMFM) recommends that TAC be offered to patients with this specific history. This recommendation does not mean that every pregnancy complication after a vaginal cerclage automatically requires abdominal surgery. The specialist must review the circumstances of the previous pregnancy and explain the available options.
2. Women whose cervical anatomy makes vaginal cerclage unsuitable
Previous cervical surgery, anatomical changes or insufficient accessible cervical tissue may make it difficult to place a vaginal stitch securely in some patients.
In such circumstances, an obstetrician-gynaecologist may consider whether TAC is a suitable alternative. The decision depends on the individual's anatomy, surgical history and clinical assessment.
3. Women with a history suggesting cervical insufficiency
A history of painless cervical dilation during the second trimester, certain pregnancy losses, or spontaneous early deliveries may prompt an evaluation for cervical insufficiency.
However, these events can have different causes. A history of miscarriage or preterm birth alone does not establish that TAC is needed. Depending on the findings, a clinician may discuss vaginal cerclage, cervical-length monitoring, other management options or specialist referral.
4. Women planning another pregnancy after a complicated pregnancy
Women who have experienced pregnancy loss or early delivery despite cervical treatment may benefit from preconception counselling.
A specialist can review previous ultrasound reports, operative notes, discharge summaries and pregnancy records to determine whether TAC or another management approach may be appropriate. Early consultation can also help with planning the timing of treatment and future antenatal care.
Important: A short cervix, a previous miscarriage or a diagnosis of high-risk pregnancy does not automatically mean that TAC is required. Eligibility should be determined by a qualified clinician.
What Is Cervical Insufficiency?
Cervical insufficiency is a condition in which the cervix may open too early during pregnancy, sometimes without the contractions usually associated with labour.
Possible indicators that prompt further evaluation include:
- A previous second-trimester pregnancy loss associated with painless cervical dilation.
- A history of spontaneous preterm birth.
- Previous cervical cerclage and the outcome of that pregnancy.
- Certain cervical operations or anatomical changes.
- Relevant cervical-length findings on ultrasound, interpreted alongside the patient's history.
There is no single symptom or test that determines every case. An obstetrician-gynaecologist assesses the pregnancy history, examination findings and relevant imaging to distinguish cervical insufficiency from other causes of pregnancy loss or preterm birth.
If you have experienced a second-trimester pregnancy loss or a previous early delivery, discuss your history with a qualified specialist before or early in your next pregnancy.
TAC vs Vaginal Cerclage: What Is the Difference?
Both transabdominal and vaginal cerclage aim to support the cervix, but they differ in how the stitch is placed and the situations in which each may be appropriate.
| Feature | Vaginal cerclage | Transabdominal cerclage (TAC) |
|---|---|---|
| Placement | Through the vagina | Through an abdominal surgical approach |
| Typical role | Commonly used for selected patients at risk of cervical insufficiency or preterm birth | Considered for selected patients when vaginal cerclage has failed or is unsuitable |
| Surgical approach | Usually avoids abdominal surgery | Requires abdominal surgery, either open or laparoscopic |
| Timing | Often placed during pregnancy, depending on the indication | May be placed before pregnancy or during selected stages of pregnancy |
| Removal and delivery | Often removed before labour, depending on the type and clinical circumstances | Usually remains in place, and delivery is generally by caesarean section |
| Decision-making | Depends on pregnancy history, examination and ultrasound findings | Requires assessment of the indication, anatomy, surgical risks and future pregnancy plans |
Neither option is universally better. The appropriate procedure depends on the individual's circumstances, clinical evidence and the specialist's assessment.
When Is TAC Surgery Performed?
Transabdominal cerclage may be performed before pregnancy or during pregnancy in selected circumstances. Timing depends on the clinical indication, gestational age, anatomy, technical feasibility and the surgical team's expertise.
TAC before pregnancy
For some women, TAC can be planned before conception. This may be discussed when a previous pregnancy complication or cervical anatomy suggests that an abdominal cerclage could be appropriate.
Preconception consultation allows time to review previous records, discuss surgical risks, consider alternative options and plan future pregnancy care.
TAC during pregnancy
TAC may also be considered during pregnancy in selected cases. The timing requires specialist assessment, and the potential benefits must be weighed against the risks of operating during pregnancy.
Women with a history suggesting cervical insufficiency should seek an early review rather than waiting for a complication to occur. The specialist can assess whether TAC or another approach is appropriate.
How Is Transabdominal Cerclage Performed?
TAC is a surgical procedure performed in a hospital by a suitably qualified surgical team. The exact method depends on the patient's anatomy, pregnancy status, and the team's expertise.
The general process may include:
- Preoperative assessment: The team reviews previous pregnancies, cervical procedures, imaging, medical history and current pregnancy status.
- Counselling and consent: The patient discusses the reason for TAC, alternative treatments, potential complications, recovery and future delivery planning.
- Anaesthesia and surgery: Under the planned anaesthesia, the surgeon accesses the cervix through an abdominal approach.
- Placement of the stitch: Cerclage material is positioned around the cervix at the appropriate level.
- Postoperative monitoring: The clinical team monitors recovery and provides instructions about medication, activity, follow-up, and warning signs.
TAC may be performed through open surgery or laparoscopy. The appropriate approach depends on factors such as gestational age, anatomy, technical feasibility, available resources, and surgical expertise.
Patients should ask their treating team which approach is appropriate for their particular circumstances.
What Are the Risks of TAC Surgery?
Like other surgical procedures, transabdominal cerclage carries potential risks. These may include:
- Bleeding.
- Infection.
- Injury to nearby structures.
- Anaesthesia-related complications.
- Surgical or postoperative pain.
- Complications related to the underlying pregnancy.
- The need for additional treatment if a complication occurs.
TAC also has important implications for future pregnancy management. Because the stitch is usually left in place, delivery generally requires a caesarean section. TAC has greater surgical morbidity than a vaginal approach, so it should be considered when the expected benefits justify the risks.
Your specialist should explain which risks are most relevant to your circumstances and how complications would be managed.
Recovery After TAC Surgery
Recovery varies depending on whether TAC is performed through open surgery or laparoscopy, the patient's general health, and whether the procedure is performed during pregnancy.
After surgery, the clinical team will explain:
- Wound care and pain management.
- Activity restrictions and when normal activities may resume.
- Medication instructions.
- Follow-up appointments.
- Pregnancy planning and monitoring, where relevant.
- Symptoms that require urgent medical attention.
Follow your own discharge instructions rather than relying on a general online recovery timeline. Do not begin strenuous activity or change prescribed medication without advice from your treating team.
Seek urgent medical assessment if you develop severe or worsening abdominal pain, heavy bleeding, fever, fluid leakage during pregnancy, contractions or other symptoms your clinical team has identified as concerning.
Pregnancy After Transabdominal Cerclage
Pregnancy after TAC requires an individualised plan with an obstetrician-gynaecologist and, when appropriate, a maternal-fetal medicine specialist.
The care plan may include:
- Preconception counselling and pregnancy planning.
- Early confirmation of pregnancy and review of medical history.
- Antenatal appointments and monitoring appropriate to the clinical circumstances.
- Guidance on symptoms that require urgent assessment.
- Delivery planning and the timing of caesarean birth.
TAC is intended to reduce risks associated with cervical insufficiency in appropriately selected patients. It cannot guarantee that a pregnancy will continue to term or that complications will not occur.
Is a C-section necessary after TAC?
In most cases, yes. Because the abdominal cerclage is usually left in place, delivery is generally planned by caesarean section. The timing should be decided by the treating obstetric team based on the patient's circumstances and applicable clinical guidance.
Can TAC remain in place for future pregnancies?
TAC is generally designed to remain in place rather than being routinely removed at the end of each pregnancy. It may therefore be relevant to future pregnancies. Decisions about pregnancy planning, complications, or removal must be made with the treating specialist.
How to Choose a TAC Specialist in Delhi
Choosing a provider for TAC surgery in Delhi involves more than comparing hospital names or online rankings. Consider these questions during your consultation:
- Does the clinician have appropriate qualifications and experience in managing cervical insufficiency and cerclage?
- Can the team explain why TAC may or may not be suitable for your history?
- Are open and laparoscopic approaches discussed where relevant?
- Are the potential risks, alternatives, and implications for future delivery clearly explained?
- Is appropriate perioperative monitoring and follow-up available?
- Can the team review your previous pregnancy and surgical records?
- Are the expected costs, inclusions and follow-up arrangements explained before treatment?
If you are seeking cervical insufficiency treatment in Delhi, bring previous ultrasound reports, discharge summaries, operative notes, and pregnancy records to your consultation. These documents may help the clinician make a more informed assessment.
TAC Surgery in Delhi: Enquiries at Sunrise Hospital
Sunrise Hospital is located in Kalindi Colony, near New Friends Colony, New Delhi. Patients researching TAC surgery, cervical cerclage and related gynaecological care can contact the hospital to enquire about consultation availability and the appropriate specialist pathway.
Before recommending treatment, the clinical team should review the patient's history and explain the available options, expected benefits, risks and follow-up requirements. Confirm directly with the hospital whether the required TAC procedure, surgical approach, and specialist services are currently available.
Hospital: Sunrise Hospital
Address: F-1, Kalindi Colony, New Delhi, Delhi 110065, near New Friends Colony
General enquiries: +91-9800001900
Emergency contact: +91-9800001901
Email: helpdesk@sunrisehospitals.in
To enquire about a consultation, visit the Sunrise Hospital appointment page or the contact page.
You can also explore the hospital's obstetrics and gynaecology services and cervical cerclage information, where the pages accurately describe the services currently provided.
Frequently Asked Questions About TAC Surgery
1. Who may need transabdominal cerclage?
TAC may be considered for selected women who have experienced a very early spontaneous delivery despite a previous vaginal cerclage, or whose cervical anatomy makes a vaginal stitch unsuitable. A specialist must assess the patient's history and circumstances before recommending it.
2. Is TAC recommended after a failed vaginal cerclage?
It may be. The Society for Maternal-Fetal Medicine recommends offering TAC to patients who had a previous vaginal cerclage and subsequently experienced a spontaneous singleton delivery before 28 weeks. The decision still requires specialist counselling and consideration of the individual case.
3. Does a short cervix mean I need TAC surgery?
No. A short cervix does not automatically mean TAC is necessary. Depending on the patient's history and ultrasound findings, a clinician may discuss monitoring, vaginal cerclage, medication or other management options.
4. Can TAC be performed before pregnancy?
Yes. TAC can be performed before pregnancy in selected patients. Preconception planning allows the clinician to assess the indication, discuss the risks, and explain the implications for future pregnancy and delivery.
5. Can TAC be performed during pregnancy?
It can be considered in selected circumstances. Timing depends on gestational age, the patient's condition, the indication, and the clinical team's assessment. Prompt specialist consultation is important.
6. Is TAC better than vaginal cerclage?
Neither procedure is best for every patient. Vaginal cerclage is the more common approach, while TAC is generally reserved for selected patients in whom a vaginal stitch has failed or is unsuitable.
7. What are the main risks of TAC surgery?
Potential risks include bleeding, infection, injury to nearby structures, anaesthesia-related complications and postoperative pain. TAC also usually means delivery must occur by caesarean section. Your clinician can explain the risks relevant to your medical history.
8. Is a C-section required after TAC?
In most cases, yes. Since TAC is generally left in place, delivery is usually by caesarean section. Your treating obstetrician will plan the timing and delivery approach.
9. How much does TAC surgery cost in Delhi?
The cost depends on factors such as the surgical approach, hospital charges, anaesthesia, investigations, length of stay, and follow-up needs. Contact the hospital for a current estimate based on your individual treatment plan rather than relying on an unverified online price.
10. Where can I enquire about TAC surgery in Delhi?
You can contact Sunrise Hospital, F-1, Kalindi Colony, New Delhi, Delhi 110065, near New Friends Colony, at +91-9800001900 or helpdesk@sunrisehospitals.in to enquire about consultation availability and the appropriate specialist.
Conclusion
Transabdominal cerclage can be an important option for selected women with cervical insufficiency, particularly when a previous vaginal cerclage has not been successful or cervical anatomy makes a vaginal approach unsuitable. However, TAC involves abdominal surgery, carries potential risks, and generally requires caesarean delivery.
If you are considering TAC surgery in Delhi, seek an individual assessment from a qualified specialist. A careful review of your previous pregnancies, cervical procedures and current health can help you understand whether TAC or another treatment approach is appropriate.
Medical disclaimer: This article is for general educational purposes only and does not replace medical advice, diagnosis or treatment. The suitability, timing, and method of TAC must be determined by a qualified clinician after reviewing the patient's individual circumstances.




